Cycle Syncing When Your Strength Numbers Drop: Deload or Push Through?
Quick Answer: A 5-10% drop in working weights during the late luteal phase is a normal, well-documented pattern and not a sign your program failed. The distinguishing feature is timing - hormonal dips arrive on a predictable schedule and resolve within days of your period starting. Actual detraining or under-recovery does not track your cycle. Log the phase alongside the weight for two full cycles, and you will be able to tell them apart at a glance.
Nothing derails a strength program faster than a week where everything feels heavy. If you have ever restarted a linear progression from scratch because of one bad week, this is the framework that stops that from happening again.


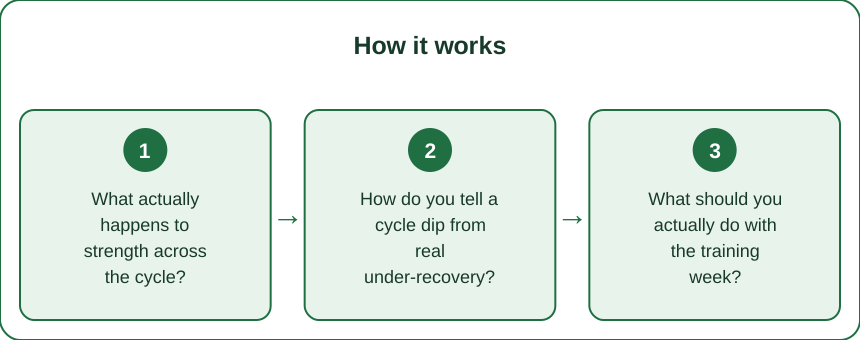
What actually happens to strength across the cycle?
The honest summary of the research is: the effects are real but smaller and more individual than popular content suggests.
What is reasonably well supported:
- Follicular phase (roughly days 1-14): rising estrogen is associated with favorable conditions for strength and power work in many studies. Some research finds higher strength gains from follicular-phase-emphasized training, though the effect sizes vary considerably.
- Ovulation (around day 14): often reported as a peak, though also the point at which some studies note increased laxity in connective tissue.
- Luteal phase (roughly days 15-28): rising progesterone increases core body temperature by about 0.5-1.0F, raises resting heart rate, and increases perceived exertion at the same absolute workload. The same weight genuinely feels heavier.
- Late luteal / premenstrual week: the most commonly reported dip, driven by a combination of sleep disruption, thermoregulation, and perceived exertion rather than a large drop in actual force production.
The critical nuance: the effect on perceived effort is more consistent than the effect on maximum force. Many women can still hit their numbers in the late luteal phase - it just costs more subjectively, which changes whether they attempt the set at all.
The variation between individuals is also larger than the variation across the cycle for many people, which is why your own data beats any general chart.
How do you tell a cycle dip from real under-recovery?
Three tests, in order of usefulness.
1. Does it track the calendar? Log your cycle day next to every session weight for two full cycles. A hormonal pattern shows up in the same window each time. Under-recovery from too much volume or too little food shows up progressively and does not care what day it is.
2. Does it resolve on its own? A late luteal dip typically lifts within 1-3 days of your period starting. If the heaviness persists into the follicular week, the cycle is not the explanation.
3. What else is doing it? Under-recovery has a signature cluster: resting heart rate elevated for several days, sleep quality dropping, motivation gone, small niggles appearing, appetite either suppressed or wildly increased. A hormonal dip usually shows fewer of these and, importantly, the warm-up sets still feel normal - it is the top sets that suffer.
A useful reframe: these two things are not mutually exclusive. The late luteal week is when accumulated fatigue is most likely to surface, because you have less buffer. So a dip that arrives on schedule and comes with poor sleep and high resting heart rate is probably both, and the answer is the same either way - reduce load, keep the movement pattern, and reassess in a week.

What should you actually do with the training week?
The best answer is usually not deload, and not push through, but modify.
Keep the movement, reduce the load. Instead of skipping squats, squat at 80% of your usual working weight for the same sets and reps. You maintain the motor pattern, the frequency, and the habit, and you avoid the psychological hit of a failed session.
Shift the metric. If your program calls for a top set at RPE 8, keep the RPE and let the weight fall where it falls. Autoregulation solves this problem cleanly - RPE-based programming absorbs cycle variation automatically in a way that fixed percentages cannot.
Move volume rather than removing it. If the late luteal week is consistently your hardest, structure the mesocycle so that it lands on a planned lighter week. Aligning your programmed deload with your late luteal phase is the single most practical application of cycle syncing for a lifter.
Do not test maxes in the week you already know is your worst. This sounds obvious and is routinely ignored. Testing in your follicular phase and deloading in your late luteal phase means your program’s data points come from comparable conditions.
What not to do: restart a progression, change programs, cut calories further, or add cardio to compensate. All four make the next cycle worse.
What Nobody Tells You About Cycle Syncing and Real Life
The cycle syncing content ecosystem has a quiet assumption baked into it: that you have a regular 28-day cycle, no hormonal contraception, and complete control over your training schedule. Very few people have all three.
If you are on hormonal contraception, most combined pills suppress the natural fluctuation substantially. The pattern you experience is driven by the pill regimen, not by a natural cycle, and syncing to a standard four-phase model does not apply. Track your own pattern instead.
If your cycle is irregular, retrospective syncing does not work. What still works is logging symptoms and performance and looking for your own recurring pattern, even if it is not on a 28-day clock.
If you train in a group class or with a partner, you cannot reschedule your heavy day around day 24. What you can do is autoregulate within the session.
And the honest limitation: the research base for cycle-based training periodization is genuinely thin. Sample sizes are small, phase verification is often done by counting days rather than measuring hormones, and results conflict. The reasonable position is that cycle-aware training is a useful lens for interpreting your own data, not a prescription with strong evidence behind it.
What has much stronger evidence: sleeping enough, eating enough protein, and not restarting your program every time a week goes badly.
FAQ: Cycle and Strength Questions, Answered
Should I stop lifting during my period?
No evidence supports stopping. Many women report that the first days of a period actually feel better than the days before it, as progesterone drops. Train by feel, and expect the follicular week that follows to be a strong one.
Does iron loss during menstruation affect training?
It can, particularly with heavy periods. Low ferritin causes fatigue and reduced endurance capacity well before it causes clinical anemia. If you have heavy bleeding and persistent fatigue, a ferritin test is worth asking your doctor for. This is general information, not medical advice.
Is it true that injury risk is higher around ovulation?
Some research associates the estrogen peak with increased ligament laxity and a higher rate of ACL injury in that window, mostly studied in cutting and landing sports rather than lifting. For barbell work in controlled planes of motion, the practical implication is small - warm up properly and do not chase a max on a day your knees feel loose.
How many cycles of data do I need before the pattern is real?
Two is enough to see a suggestion, three is enough to act on. Log cycle day, session RPE, top set weight, and sleep hours. Four data points per session and a pattern usually appears by the third cycle.
TL;DR:
- A 5-10% dip in the late luteal week is normal and mostly a perceived-effort effect, not lost strength.
- Distinguish it from under-recovery by whether it tracks the calendar and resolves when your period starts.
- Modify rather than skip: same movement, 80% load, or switch to RPE-based autoregulation.
- Align your programmed deload with your worst week and test maxes in your best one.
The most useful thing cycle syncing offers a lifter is not a phase-specific workout plan. It is permission to stop treating one bad week as evidence that the program is broken.
Keep Reading
This article is for general informational purposes only and is not medical advice. Always consult a qualified health professional for guidance specific to you.
